Diabetes: India’s Silent Epidemic—Why the Order You Eat Matters

Practical Steps to Improve Blood Sugar and Prevent Progression
Dr. Fayaz Shawl, MD, FACP, FACC, FSCAI
(Clinical Professor of Medicine, George Washington University; Director, Interventional Cardiology, Adventist HealthCare White Oak Medical Center, USA; Founder, The Fayaz Shawl Philanthropic Foundation)
PART A
Improving Glucose Control Through Food Choices and Post-Meal Activity
The magnitude of diabetes in India
Diabetes is one of the largest chronic-disease challenges of our time. The World Health Organization reports that approximately 830 million people worldwide were living with diabetes in 2022. India has the second-largest number of adults with diabetes in the world, after China. The International Diabetes Federation estimates that about 90 million Indian adults aged 20 to 79 had diabetes in 2024, compared with 148 million in China, and that this number may reach about 157 million by 2050. Nearly half of Indian adults with diabetes, about 43 percent, do not know they have it. India’s own national survey, the ICMR-INDIAB study, used different methods and estimated an even higher figure: about 101 million Indians, 11.4 percent of adults, had diabetes in 2021. These estimates use different age ranges, diagnostic criteria and methods, so they should not be directly compared or interpreted as changes over time. Each number represents a person at risk of heart attack, stroke, kidney disease, vision loss, neuropathy and premature death.
No community is protected. Diabetes is no longer only a disease of cities or of the wealthy: it is rising in smaller towns and villages, and many people remain undiagnosed until a complication appears. Indians tend to develop diabetes about a decade earlier and at a lower body weight than many Western populations, often because of abdominal fat and insulin resistance. This is why the Fayaz Shawl Philanthropic Foundation is developing this education series: to promote earlier testing and practical guidance on food, portions, meal sequence, medication safety and activity alongside medical care.
A family experience
For more than 40 years as a cardiologist, my philosophy has been to care for every patient as I would care for my own family. If you treat everyone like family, you will do your best for them. That principle guided the experience I describe here.
When someone close to us develops poorly controlled diabetes, prompt action matters, and so does accuracy. After studying the research on meal sequence, I first used it to help my own sister. She had an HbA1c of 8.9 percent, well above the usual treatment target. Her seven-day continuous glucose monitor (CGM) report for 6–12 September 2026 showed an average glucose of 181 mg/dL, with evening averages reaching 205 and 220 mg/dL.
Alongside her medical care, we made structured changes to meal composition, portion size, food order and post-meal activity, with close supervision and continuous glucose monitoring. Her next seven-day report, for 14–20 September 2026, showed an average glucose of 133 mg/dL, a fall of 48 mg/dL, with three-hour averages between 115 and 147 mg/dL. As her glucose improved, I reduced her glucose-lowering medication, including insulin, under close supervision.
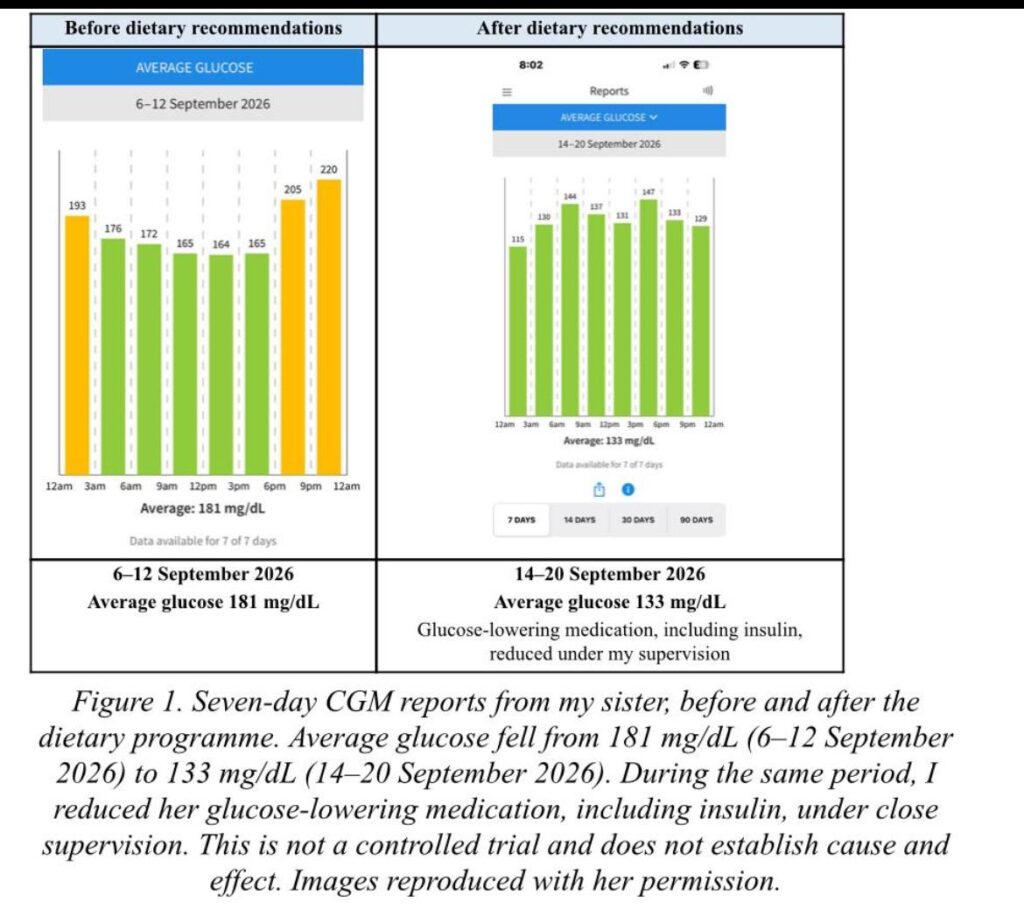
The response is encouraging, but medication, activity, adherence, sleep, illness and other factors also affect glucose. It is not proof that diabetes has been cured or reversed. HbA1c reflects glucose exposure over about three months, so a repeat laboratory HbA1c is essential. International consensus defines type 2 diabetes remission as an HbA1c below 6.5 percent for at least three months without glucose-lowering medication, and even then, continued monitoring is necessary because high blood sugar can return.
A CGM is useful for recognizing patterns and testing how an individual responds to meals. It does not by itself diagnose remission, and a single low or normal reading should never be treated as proof that diabetes has disappeared.
My purpose in sharing this experience is practical: relatively simple habits can improve daily glucose patterns, but they must complement appropriate medical treatment rather than replace it.
A practical evidence-based regimen
1. Begin with a medical assessment. Confirm the type of diabetes and review HbA1c, fasting glucose, kidney function, urine albumin, blood pressure, lipids, weight and current medication. An HbA1c of 7 percent or higher deserves active treatment and follow-up. Lifestyle measures may improve control, but medication may still be necessary to protect the heart, kidneys, eyes and nerves.
2. Use nuts as a measured food. Walnuts and almonds provide unsaturated fat, fiber, magnesium and protein. A small serving of about 20 grams (roughly 10 almonds and 4 walnut halves, depending on their size) taken 20 to 30 minutes before a meal may reduce the post-meal glucose rise in some people, particularly when it replaces biscuits, namkeen or fried snacks. A randomized trial in India, in adults with prediabetes, found benefit from 20 grams of almonds taken 30 minutes before meals. The almond-and-walnut mixture is my practical suggestion; this exact combination and the 20-minute interval were not tested in that trial. Take the nuts with a glass of water and chew them well. Water supports hydration and may help you feel full sooner, but it has not been shown to lower glucose further. People who have been told to restrict their fluids should follow the advice in step 7. Nuts are calorie-dense and should be counted within the daily food plan. People with a nut allergy should avoid them.
3. Eat vegetables and protein before starch. Small crossover studies show that eating non-starchy vegetables and protein before carbohydrate can reduce the immediate rise in glucose and insulin after a meal. Fiber, protein and fat can influence digestion and stomach emptying, which may help glucose enter the blood more gradually. A practical sequence is a salad such as kachumber, or a cooked vegetable such as palak, methi, bhindi, lauki, gobhi or beans, first, alone or with a modest serving of plain curd or raita; then protein; and a limited amount of rice or roti last. For vegetarians, the protein can be dal, paneer, chana, rajma, soy, tofu or sprouts. For non-vegetarians, it can be chicken, fish or eggs, with mutton in moderate portions.
4. Choose plain curd when it fits the meal. Plain unsweetened curd (Dahi) supplies protein, and hung curd, which is strained, supplies even more. It generally causes only a small rise in blood sugar. In my clinical observation with CGMs, mixing a modest serving of plain curd with greens or other non-starchy vegetables at the start of the meal was associated with a smaller post-meal glucose rise. In practice, this can be a bowl of cucumber or vegetable raita, or a spoonful of curd with the sabzi, at the start of the meal. Unsweetened chaas (buttermilk) is also a good choice. This combination has not been tested in a controlled trial, so it is a practical observation rather than a proven treatment. Avoid sweet lassi, flavored yogurts and sweetened curd, and do not add sugar, honey or jaggery. Portion size and total calories still matter. People with lactose intolerance or dairy allergy need an alternative.
5. Reduce rapidly digested carbohydrate without unnecessary prohibitions. White rice, Maida products such as naan, white bread and bhature, poha, sugary cereals, bakery items and sweets can cause large glucose rises, especially in generous portions. The most important step is to reduce quantity and frequency. A small measured serving of rice, or one or two small whole-wheat or millet rotis (jowar, bajra or ragi), depending on your needs, may fit an individual plan when eaten after vegetables and protein. Millet flour still contributes carbohydrate; roti size, flour quantity and your own glucose response matter. Mithai, Gulab jamun, jalebi, halwa and kheer should be occasional foods, not daily staples. Jaggery (gur) and honey raise blood sugar much like sugar, and fruit juice raises it faster than whole fruit, so choose a piece of fruit rather than juice.
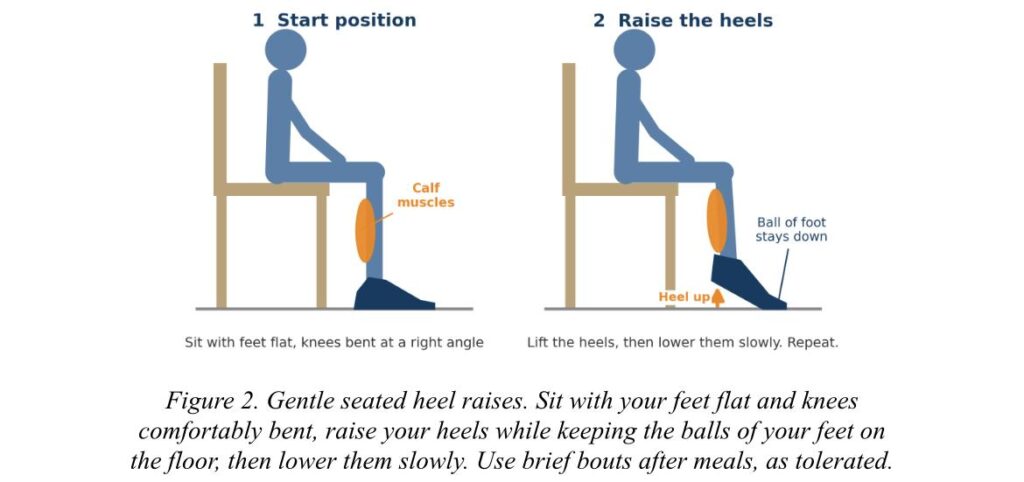
6. Walk after meals, or exercise your calves while seated. A 10- to 15-minute walk soon after a meal can lower post-meal glucose. Working muscles draw sugar out of the blood, partly without needing insulin. This helps, but it does not replace diabetes treatment. A randomized crossover study found that short walks after each main meal improved post-meal glucose more than a single daily walk. If walking is difficult, gentle seated heel raises after meals may provide a practical movement break. Sit with your feet flat on the floor, slowly raise your heels while keeping the balls of your feet on the ground, and lower them comfortably. Use brief bouts after meals, as tolerated, and stop if they cause pain. Research on a specialized soleus exercise is promising, but ordinary heel raises have not been shown to reproduce the same results. They complement walking and other suitable activity. The science and its limitations are explained in Part C.
7. Stay appropriately hydrated. Water is preferable to sweetened drinks, and dehydration can worsen illness when blood sugar is very high. Fluid intake must be individualized in people with heart failure, kidney disease, liver disease or a tendency toward low sodium. In India’s summer heat, fluid needs rise, especially for people who work or exercise outdoors.
8. Measure the result over time. Review CGM patterns over at least 10 to 14 days when available, confirm unexpected readings with a finger-stick meter, and repeat HbA1c after about three months. Follow weight, waist circumference, blood pressure, kidney health and medication needs as well as glucose.
Medication safety
Do not reduce or stop prescribed medication or insulin on your own. Better food choices and more activity can lower glucose quickly, especially in people taking insulin or sulfonylureas such as glimepiride or gliclazide, and these medicines may need supervised adjustment to prevent hypoglycemia. In my sister’s case, I made those adjustments myself as her physician, with continuous monitoring. Other medicines may remain important because they protect the heart and kidneys even when glucose improves.
Blood sugar and body weight
Many people ask whether lowering blood sugar will also reduce their weight. The answer depends on how the sugar is lowered. Lower glucose does not, by itself, melt away weight.
Weight loss lowers blood sugar. The evidence is strongest in this direction. In the DiRECT trial in the United Kingdom, a structured low-calorie programme brought about remission of type 2 diabetes in 46 percent of participants at one year, and in 86 percent of those who lost 15 kilograms or more. Even modest weight loss of 5 to 7 percent improves glucose, as the Diabetes Prevention Program showed.
Medicines lower glucose in different ways, with different effects on weight. Insulin and sulfonylureas such as glimepiride and gliclazide often cause weight gain of a few kilograms. Part of the reason is that when glucose is very high, the body loses calories as sugar in the urine; once glucose is controlled, those calories are kept. Metformin is roughly weight-neutral or causes modest weight loss. SGLT2 inhibitors, such as empagliflozin and dapagliflozin, remove sugar through the urine and usually reduce weight by 2 to 3 kilograms. GLP-1-based medicines reduce appetite: in large trials in people with obesity, semaglutide produced weight loss of about 15 percent and tirzepatide of up to about 21 percent. Their weight loss comes mainly from reduced appetite, not from the lower glucose itself.
Smoother glucose may help appetite, but the evidence is still developing. In a study of 1,070 adults wearing glucose monitors, those whose glucose dipped sharply two to three hours after a meal felt hungrier, ate sooner and consumed more calories later in the day. However, another carefully controlled study found that people ate several hundred fewer calories a day on a low-fat, higher-carbohydrate diet than on a low-carbohydrate diet, despite higher glucose and insulin levels. Glucose patterns alone do not determine how much we eat.
What this means for meal sequence. No long-term trial has shown that eating in the right order, by itself, causes significant weight loss; its proven benefit is a smaller rise in glucose after meals. It may help with weight indirectly. Starting with vegetables, protein and a few nuts increases fullness and makes a smaller portion of rice or roti easier to accept, and walking after meals adds daily activity. Lasting weight loss still depends on total calories, food quality, activity, sleep and, for some people, medication.
If your glucose improves but your weight rises, discuss it with your doctor, because your medication plan may need review.
Religious fasting
Many people with diabetes observe fasts, such as Navratri, Ekadashi, Karva Chauth, Ramadan or Jain fasts. Anyone with diabetes who plans to fast should see their doctor six to eight weeks beforehand to assess the risk and adjust medication, particularly insulin and sulfonylureas. Check glucose regularly while fasting; a finger-stick or sensor check does not break the fast. International guidelines for Ramadan fasting offer a sensible guide for other fasts too: they advise ending the fast immediately if glucose falls below 70 mg/dL or rises above 300 mg/dL, or if symptoms of low or high blood sugar appear. Traditional fasting foods such as sabudana, kuttu and singhara flour, potatoes and sweets are rich in carbohydrate, so the same principles apply: begin with vegetables, curd, paneer or nuts, keep the starchy portion small and avoid sweet drinks. Fasts without water, such as Karva Chauth, carry an added risk of dehydration and need particular care.
The main lesson
The family experience shows how quickly daily glucose patterns can respond to a disciplined routine. It does not establish a cure. The clinically meaningful questions are whether the improvement is sustained, whether HbA1c falls over the next three months, whether medication can be adjusted safely and whether cardiovascular and kidney risk factors also improve.
PART B
Prediabetes Is a Warning and an Opportunity for Prevention
The magnitude of prediabetes
The population at risk is even larger than the number already diagnosed with diabetes. The ICMR-INDIAB study estimated that about 136 million Indians, 15.3 percent of adults, had prediabetes in 2021, more than the 101 million who already had diabetes. Most people in this intermediate stage have no symptoms, and many do not know that their glucose is abnormal.
Using HbA1c, prediabetes generally means a laboratory value from 5.7 to 6.4 percent. A value of 5.7 percent is the lower boundary, not a medical emergency, while 6.5 percent or higher may meet a diagnostic criterion for diabetes when confirmed. In a person without symptoms, an abnormal result should generally be confirmed with a repeat HbA1c or another laboratory glucose test. Anemia, kidney disease and some hemoglobin variants can affect HbA1c accuracy.
Prediabetes should not be described as harmless, but neither is progression to diabetes inevitable. It is a warning and, more importantly, an opportunity for prevention.
The International Diabetes Federation estimated that in 2024 approximately 635 million adults worldwide had impaired glucose tolerance and 488 million had impaired fasting glucose. These categories overlap, and they are not identical to HbA1c-defined prediabetes, so the two figures must not be added together. They nevertheless show the enormous global pool of people at increased risk of type 2 diabetes.
This is precisely the population I would like to educate. People with an HbA1c between 5.7 and 6.4 percent may feel completely well while insulin resistance is progressing. Timely education about familiar, everyday food choices, sensible carbohydrate portions, regular activity, weight management when needed and appropriate medical follow-up can help many of them delay or prevent type 2 diabetes.
During more than four decades as an interventional cardiologist, I have seen the consequences of diabetes in the arteries of the heart, brain, kidneys and legs. Prediabetes deserves attention because it identifies people at increased risk of type 2 diabetes and cardiovascular disease. It is also a stage at which prevention can be highly effective.
Current medical care does not recommend waiting passively for diabetes to develop. It recommends weight management when needed, healthier food choices, regular physical activity and periodic testing. Metformin may also be considered for selected people at particularly high risk.
Prevention is effective, but cure is not the right term
Prediabetes can return to the normal glucose range, and progression to type 2 diabetes can often be delayed or prevented. The word cure is misleading because insulin resistance and future risk may remain. The landmark Diabetes Prevention Program found that an intensive lifestyle programme reduced the development of type 2 diabetes by 58 percent over approximately three years. Participants aimed for 7 percent weight loss and at least 150 minutes of physical activity each week. Closer to home, the Indian Diabetes Prevention Programme found that lifestyle change reduced progression to diabetes by about 28 percent in Indian adults with impaired glucose tolerance. Ask your doctor about structured diabetes education or prevention programmes available through your hospital or clinic.
Why I am sharing this message
Prediabetes is a common precursor to type 2 diabetes, although progression is not inevitable. Early action offers a real opportunity to interrupt that progression. In my clinical experience, many patients who closely followed structured dietary recommendations and regular exercise saw their HbA1c return to the normal range, below 5.7 percent, within approximately six to nine months. This should be confirmed by repeat laboratory testing and does not mean that future diabetes risk has disappeared.
A few of my close friends had an HbA1c of 5.7 percent. With their permission, I reviewed their CGM patterns. After reducing cereal portions and combining carbohydrate with nuts, berries and unsweetened Greek yogurt, they saw smaller peaks after breakfast and average glucose levels near 100 mg/dL. At an Indian breakfast, the same principle means a smaller portion, for example one paratha instead of two, or two idlis instead of four, taken with eggs, paneer bhurji, sprouts, a bowl of sambar or plain curd. Paratha and idli sizes vary considerably, so let size, ingredients and your own glucose response guide the portion.
These observations are encouraging, but they are not a controlled trial and cannot predict every person’s result. A single CGM value cannot diagnose or exclude prediabetes. Follow-up should include repeat laboratory HbA1c and assessment of weight, waist circumference, blood pressure, lipids and overall cardiovascular risk.
A practical prevention plan
1. Know the baseline. Check laboratory HbA1c or fasting glucose and confirm an abnormal result when appropriate. Measure blood pressure, weight, waist circumference and lipids. India’s national screening programme offers testing to adults from age 30. Testing should be earlier for adults with overweight or obesity plus another risk factor, such as a family history, previous diabetes in pregnancy, high blood pressure, abnormal lipids or physical inactivity. For Indians, overweight begins at a BMI of 23, [19] and a waist above about 90 cm in men or 80 cm in women signals abdominal obesity, [20] because Indians often develop diabetes at lower weights.
2. Change portions before giving up favourite foods. Familiar foods can remain part of a healthy plan. Fill about half the plate with non-starchy vegetables. Keep rice, roti, paratha and potatoes to small, measured portions, about a quarter of the plate. Reduce sweetened chai, soft drinks, fruit juices, mithai and bakery biscuits. Fried foods such as samosa, pakora, puri, bhature and kachori, and rich dishes such as biryani, butter chicken and paneer makhani, should be eaten in moderate portions because they may contain large amounts of refined carbohydrate, saturated fat and salt. At weddings and buffets, fill the plate first with salad, dal, paneer or chicken, and take rice, naan and sweets last and in small amounts.
3.Use food order as an additional tool. Start with vegetables, alone or with a modest serving of plain curd or raita; follow with dal, paneer, chana, chicken, fish or eggs; and take rice or roti last. This may blunt the post-meal rise, but it does not make an unlimited carbohydrate portion safe.
4. Choose snacks that replace refined carbohydrate. A measured portion of unsalted walnuts or almonds can replace biscuits, namkeen or samosas at tea time. Roasted chana, unsalted peanuts, sprouts and plain curd or chaas are affordable alternatives. Tea and coffee contain little carbohydrate without sugar, but several cups of sweetened chai a day, taken with biscuits, add up quickly. Evidence does not support relying on cinnamon or green tea as diabetes treatment. [21]
5. Move after meals and throughout the week. Walk for 10 to 15 minutes after meals when safe. Aim for at least 150 minutes of moderate activity each week and include muscle-strengthening exercise two or three times weekly. People with heart symptoms, severe neuropathy, foot ulcers or major mobility limitations should get individual exercise advice. During the summer heat or monsoon rains, walk indoors at home, on a terrace or in a building corridor, or outdoors early in the morning or after sunset.
6. Address the major drivers of risk. If excess weight or abdominal fat is present, even modest weight loss can improve insulin sensitivity. Preserve muscle with adequate protein and strength exercise. Sleep regularly, avoid tobacco and treat high blood pressure and abnormal cholesterol.
7. Repeat laboratory testing. Recheck HbA1c about three months after a major lifestyle change. People with confirmed prediabetes should usually be tested at least yearly, with the interval set by their doctor.
8. Use AI or a quick search when eating out. Before or during a restaurant meal, or when ordering through a food delivery app, give an AI assistant on your phone the name of the restaurant and ask, for example: “I have diabetes or prediabetes. What should I order at [restaurant name] to avoid a large blood sugar spike?” You can also search a menu item online with the question “Is [dish] good for diabetes?” Many chain restaurants also publish nutrition information, including carbohydrate content, on their websites. Treat these answers as a helpful starting point rather than medical advice: AI tools can make mistakes, and menus and portion sizes change. Then apply the same principles at the table: start with a salad or vegetables, choose a protein-based main dish, skip or limit the bread basket, ask for sauces and dressings on the side, and take part of a large portion home.
A message for the public
Prediabetes is neither a reason for panic nor a reason for inaction. It is an opportunity to intervene early. Sustainable food choices, weight management when needed, regular activity and appropriate medical follow-up can substantially reduce risk. Medication is sometimes appropriate and should never be seen as failure. The goal is lasting metabolic and cardiovascular health, not a perfect single sensor reading.
PART C
How the Programme Works: The Science Behind Each Step
Research supports several elements of this programme, and its central finding is consistent: eating vegetables and protein before carbohydrate lowers the rise in glucose after a meal. The complete sequence described here has not been tested as one intervention, and the explanations below combine established physiology with mechanisms that are still being studied. The limitations are summarized at the end of this section.
1. Nuts before the meal: a possible brake on digestion. The fat, protein and fiber in almonds and walnuts may influence fullness and the rate at which food leaves the stomach. Gut hormones may contribute, including cholecystokinin (CCK) and glucagon-like peptide-1 (GLP-1), the hormone that newer medicines such as semaglutide act on. Chew nuts thoroughly and include them within the daily calorie allowance. The cited trial studied 20 grams of almonds taken 30 minutes before meals in Asian Indians with prediabetes.
2. Vegetables first: fiber and meal sequence. Palak, methi, bhindi, lauki, karela, cabbage, beans and salads such as kachumber supply fiber. Some soluble fibers absorb water and thicken the digestive contents, which can slow the absorption of sugar from starch eaten later in the meal; insoluble fiber adds bulk and fullness. Starting with vegetables also helps people eat more vegetables and keep the starch portion smaller.
3. Plain curds: protein as part of the meal. Plain curd and paneer provide milk proteins, mainly casein with some whey; strained hung curd generally contains more protein per serving than regular curd. Protein can stimulate early insulin and gut-hormone responses. A trial using a whey-protein drink before breakfast in people with type 2 diabetes reduced post-meal glucose, although a modest serving of curd cannot be assumed to have the same effect. Combining curd with vegetables reflects my CGM observations, as noted in Part A.
4. Protein, dal or paneer: fullness and slower digestion. Protein from dal, paneer, chana, rajma, soy, eggs, fish or chicken may influence stomach emptying and stimulate gut hormones such as peptide YY (PYY), which act on appetite centers in the brain to increase fullness. Feeling satisfied sooner makes it easier to keep the starch portion small. Dal, chana and rajma also contain carbohydrate, so their portions count toward the total for the meal.
5. Starch last: a lower post-meal rise. When rice or roti follows vegetables and protein, the earlier foods may slow stomach emptying and the absorption of sugar. The starch is still digested, but more gradually. In a small study in type 2 diabetes, eating protein and vegetables before carbohydrate lowered glucose by about 29 percent at 30 minutes and 37 percent at 60 minutes compared with eating carbohydrate first. In people with prediabetes, the same research team found the glucose peak was more than 40 percent lower when carbohydrate came last. Whether meal order on its own reduces heart attacks, strokes or other complications has not been proven. Large glucose swings after meals are associated with oxidative stress, so smoothing them is a reasonable goal, but this does not establish heart protection from this sequence.
6. A note on cooled rice. When cooked rice is refrigerated, part of its starch changes into resistant starch, which resists digestion in the small intestine. In one study, white rice cooled for 24 hours and then reheated produced a smaller glucose rise than freshly cooked rice. A similar change occurs when cooked potatoes are cooled. Food safety matters: cooked rice left at room temperature, especially in a warm climate, can grow bacteria whose toxin survives reheating. Put cooked rice into shallow containers and refrigerate it promptly, ideally within one hour, keeping the refrigerator at 4°C or below. Consume within 24 hours. Before eating, reheat only the portion you need until it is steaming hot throughout (74°C), eat it promptly, and do not reheat it a second time. The glucose effect is variable and is not guaranteed; cooling does not remove the carbohydrate. Portion size remains more important than cooling.
7. Walking after meals: muscles as a sugar sink. In type 2 diabetes and prediabetes, the body responds poorly to insulin, mainly because the insulin signal inside the cell is impaired. Working muscle has a second route. During walking, signals within the muscle move glucose transporters called GLUT4 to the cell surface without needing insulin, letting sugar pass from the blood into the muscle to be used as fuel. This is why a short walk after meals lowers post-meal glucose and reduces how much insulin the pancreas must produce. Even two to five minutes of light walking helps, and in summer heat or monsoon rains, walking indoors or up and down stairs works as well.
The calf muscle: promising research with a specialized technique. The soleus is a deep calf muscle rich in slow-twitch fibers. In a small University of Houston laboratory study, a specific soleus-pushup technique sustained during a three-hour glucose test reduced the incremental glucose response by up to 52 percent and the insulin response by up to 60 percent compared with sitting still. These were results for a carefully studied movement under laboratory conditions, not evidence that ordinary seated heel raises will produce the same benefit. A separate trial in adults with type 2 diabetes found that three-minute breaks every 30 minutes involving a combination of simple resistance activities, including calf raises, improved post-meal glucose; it did not isolate calf raises alone. Gentle seated movement can be a practical activity break, but no universal heel-raise duration or glucose reduction should be promised.
What these mechanisms do and do not mean
Together, these steps may help reduce post-meal glucose rises, although the exact combined programme has not been tested in a controlled trial and individual responses vary. They do not stop sugar from entering the blood, and they do not make large portions safe. They work best alongside sensible portions, regular activity, weight management when needed and appropriate medical treatment. People taking insulin or sulfonylureas should discuss these changes with their doctor, because lower post-meal glucose may require medication adjustment.
(Disclaimer: My observations come from patients using continuous glucose monitors, sensor patches worn on the arm that send readings to a mobile phone. Glucose may fall substantially after these dietary changes; individual responses vary, and this is not a controlled trial. Patients taking insulin or medicines that can cause hypoglycaemia must coordinate with their treating physician about dose adjustment. During the early dietary change, monitor glucose frequently and do additional finger-stick tests, especially at bedtime, when the sensor shows a low or rapidly falling value, or when symptoms do not match the sensor reading. Do not change medication without guidance from your treating doctor.)
(STRAIGHT TALK COMMUNICATIONS EXCLUSIVE)